
The activity and clinical context matter, not stereotypes
Either partner can acquire HIV during anal sex in relevant circumstances. Receptive anal sex generally has a higher likelihood than insertive sex because of the exposure route and susceptible tissue. Role labels, appearance, identity and partner count are not a diagnosis or a judgment of character. [1]
Old per-act percentages and multipliers do not predict your individual outcome. Assessment must include the actual event, timing and prevention, including the partner’s effective treatment where known. This article does not provide a personal risk calculator or claim that an old percentage applies to everyone. [1] [2]
U=U changes the assessment of sexual HIV transmission
A person on ART who maintains viral suppression meeting U=U criteria does not transmit HIV through sex, including anal sex. This requires ongoing treatment and clinical monitoring; it is not established from appearance, a screening test or an isolated result. [2]
U=U is not a cure and does not guarantee prevention through breastfeeding or sharing injection equipment, other STIs or pregnancy. People deserve respectful care whether or not they have achieved suppression. Ordinary social contact does not transmit HIV. [2] [1] [3]
Choose prevention with a care team
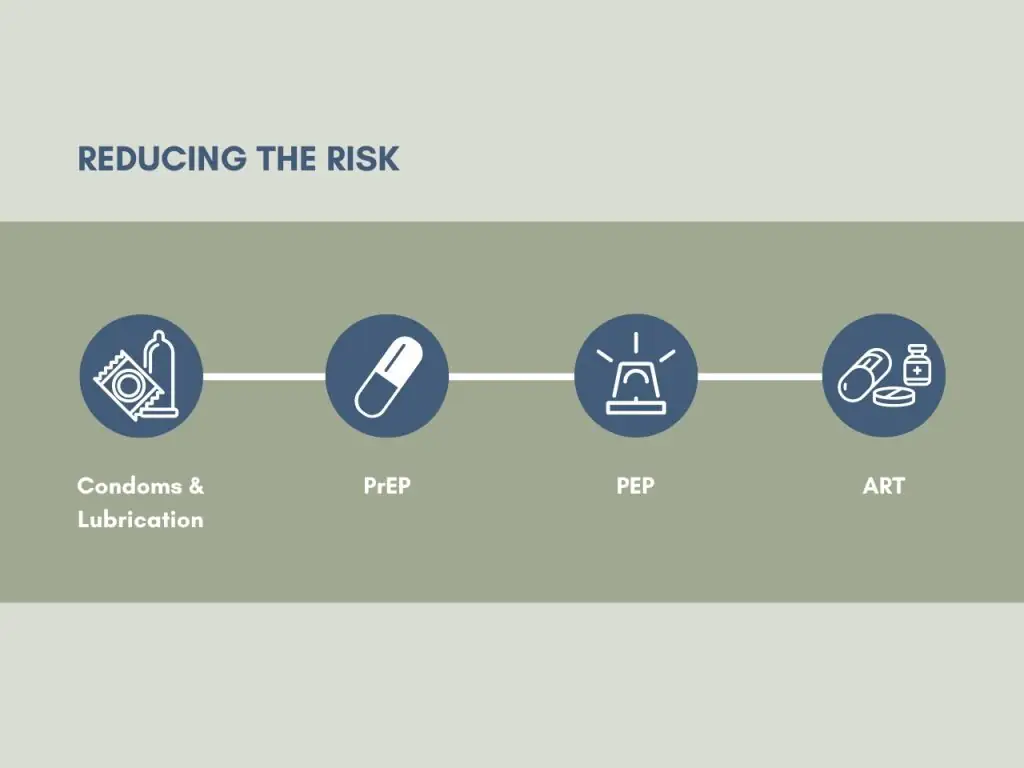
Condoms used correctly throughout sex and compatible lubricant help reduce HIV and some STI risks but do not prevent every STI. Oil-based products can weaken latex condoms. Do not translate historical condom-effectiveness figures into a guarantee for one event. [4]
PrEP is prevention before possible exposure for a person without HIV after appropriate testing and assessment. Product choice, starting, stopping and follow-up depend on individual circumstances; do not copy dosing schedules, borrow medicine or assume an injection removes the need for follow-up. [5] [6]
A recent possible exposure is time-sensitive
Seek PEP assessment immediately and start when indicated within 72 hours. Do not wait for symptoms, all laboratory results or an appointment. Seek assessment even if more time has passed, and discuss subsequent testing and prevention. This article does not prescribe a regimen or pill frequency. [7]
An early negative result may not exclude the latest event. Reactive screening results need confirmation and the follow-up plan depends on test type, timing and recent PrEP or PEP use. Testing connects people to care but does not itself prevent HIV. [6]

Do not use symptoms or unverified causal claims to diagnose
Pain, bleeding or other symptoms deserve clinical assessment rather than guessing HIV status. The previous article’s precise claims about poppers, douching or circumcision are not retained as verified causal estimates or instructions to prevent HIV. Talk with a service about the actual concern without shame or stereotypes.
Frequently asked questions
Are insertive partners immune to HIV?
No. Either partner may acquire HIV in relevant circumstances; receptive anal sex generally has a higher likelihood. The assessment still depends on the actual exposure and prevention, not a role label alone. [1]
Does an old per-act percentage predict my outcome?
No. It is not an individual probability or a diagnosis and may not reflect current prevention or effective treatment. Discuss the actual event rather than using a figure as a countdown. [1] [2]
Does U=U apply to anal sex?
Yes. A person on ART who maintains suppression meeting U=U criteria does not transmit HIV through sex. It is not a cure or a guarantee for other routes, other STIs or pregnancy. [2]
Should I wait for symptoms after an exposure?
No. Seek PEP assessment immediately and start when indicated within 72 hours, without waiting for symptoms, all laboratory results or booking. Seek care even if more time has passed. [7]
Can I choose a prevention prescription from this article?
No. Select PrEP, treatment and follow-up with a care team. Do not borrow medicine or copy dosing schedules from an article. [5] [7]
Summary
Either partner can acquire HIV during anal sex in relevant circumstances. Receptive anal sex generally has a higher likelihood than insertive sex because of the exposure route and susceptible tissue. Role labels, appearance, identity and partner count are not a diagnosis or a judgment of character. [1]
ลิงก์และภาพประกอบเดิม
เก็บลิงก์เดิมไว้สำหรับการเข้าถึงข้อมูลประกอบ ไม่ใช้รับรองคำแนะนำทางการแพทย์ ราคา หรือเงื่อนไขปัจจุบัน
หมายเหตุ บทความนี้ให้ข้อมูลความรู้ทั่วไป ไม่ใช่การวินิจฉัย และไม่ใช่คำแนะนำการใช้ยาเฉพาะบุคคล เรื่องยาและการรักษาเป็นการตัดสินใจร่วมกับแพทย์หรือเภสัชกรที่ดูแลคุณ ไม่ควรซื้อ เริ่ม หยุด หรือปรับยาด้วยตัวเอง หากมีข้อสงสัยเกี่ยวกับสุขภาพของตัวเอง ปรึกษาเจ้าหน้าที่สาธารณสุขหรือคลินิกใกล้บ้านได้เสมอ
อ้างอิงตามข้อความที่ตรวจทาน
- CDC (สหรัฐฯ): ช่องทางถ่ายทอด HIV
- NIH (สหรัฐฯ): U=U และการถ่ายทอดทางเพศสัมพันธ์
- กรมควบคุมโรค: การตีตราและเลือกปฏิบัติ ไม่ตัดสินหรือลดคุณค่าบุคคล
- CDC (สหรัฐฯ): การใช้ถุงยางและการจัดการเมื่อถุงยางแตก
- CDC (สหรัฐฯ): การประเมินและติดตาม PrEP
- CDC (สหรัฐฯ): การตรวจ HIV และช่วงหน้าต่าง
- CDC (สหรัฐฯ): แนวทาง PEP ปี 2025
ตรวจทานและปรับปรุงเนื้อหา: 27 ตุลาคม 2569